

Schedule Appointment


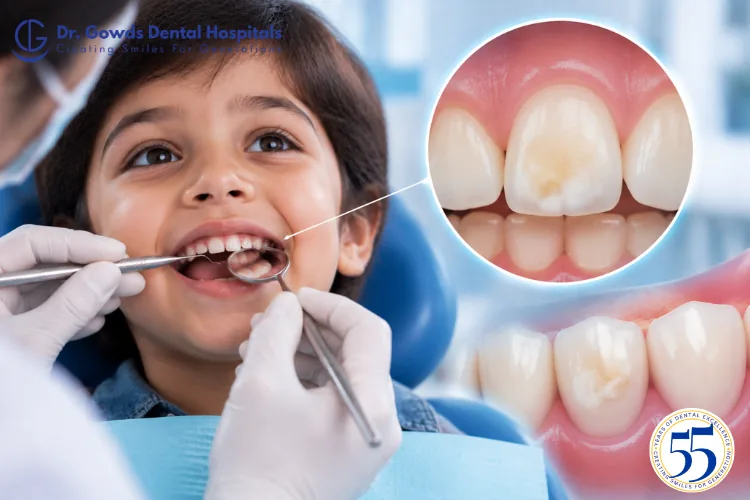
A permanent tooth is expected to develop with a relatively smooth, strong layer of enamel. But sometimes a permanent tooth erupts with an unusual appearance, such as yellow-brown discoloration, pits, grooves, or areas where the enamel appears thinner.
One possible explanation is Turner’s Tooth, a developmental enamel defect affecting a permanent tooth.
Turner’s Tooth usually develops when an infection, trauma, or other disturbance affects the baby tooth that lies above a developing permanent tooth. Because the permanent tooth is still forming underneath, the disturbance can interfere with normal enamel development.
At Dr Gowds Dental Hospitals, an unusually discolored, pitted, or malformed permanent tooth can be evaluated to determine whether the appearance is related to Turner’s Tooth, another enamel defect, tooth decay, staining, or a different dental condition.
Turner’s Tooth is named after the developmental pattern in which a permanent tooth is affected following a disturbance involving its primary predecessor.
The condition is sometimes described as Turner’s hypoplasia.
The permanent tooth itself may be healthy in terms of its root and internal structures, but the enamel can develop abnormally.
The severity can range from a small area of discoloration to a tooth with substantial enamel defects.
The key to understanding Turner’s Tooth is knowing that permanent teeth begin developing before they erupt into the mouth.
While a permanent tooth is developing beneath a primary tooth, problems affecting the baby tooth can sometimes disturb the developing permanent tooth.
For example, an infection associated with severe decay in a primary tooth may affect the enamel-forming cells of the underlying permanent tooth.
Similarly, trauma to a primary tooth can sometimes disturb the developing permanent successor.
When enamel formation is interrupted, the permanent tooth may later erupt with a visible defect.
Several events can potentially disturb the development of a permanent tooth.
A severe infection in a primary tooth is one of the important situations associated with developmental defects in the permanent successor.
When infection extends beyond the primary tooth, the developing permanent tooth underneath may be affected.
The result may become visible only years later, when the permanent tooth erupts.
An injury to a baby tooth can sometimes affect the developing permanent tooth beneath it.
Children frequently experience falls or injuries involving their front teeth. Depending on the child’s age and the stage of permanent tooth development, trauma may have different effects.
A permanent tooth that later develops an enamel defect following an injury to its primary predecessor may show features consistent with Turner’s Tooth.
Tooth enamel formation is a complex developmental process.
A significant disturbance during this stage can potentially result in an enamel defect.
However, not every discolored or pitted permanent tooth is Turner’s Tooth. A dentist needs to consider the child’s dental history and examine the tooth carefully before identifying the cause.
The appearance can vary significantly.
Affected teeth may have:
The defect may involve only a small section of the crown or a much larger portion of the tooth.
The location of the defect can sometimes provide clues about when and how the disturbance occurred during tooth development.
Turner’s Tooth can affect different permanent teeth, depending on which developing tooth was disturbed.
The front permanent teeth may be affected following trauma to primary front teeth.
Premolars may also develop enamel defects when their developing successors are affected by problems involving primary molars.
Therefore, Turner’s Tooth is not limited to one particular tooth.
The appearance and location depend largely on the tooth’s developmental stage when the disturbance occurred.
Not necessarily.
This is an important distinction.
A Turner’s Tooth may appear yellow, brown, pitted, or damaged, which can sometimes resemble dental decay.
However, the defect developed while the tooth was forming. It is different from a cavity that develops after the tooth has erupted because of bacterial activity and acid attacks.
A dental examination can distinguish developmental enamel defects from active decay.
In some cases, both conditions can occur in the same tooth, particularly if defective enamel creates areas that are more difficult to clean.
Yes.
If the enamel is significantly thin or defective, the underlying dentin may be less protected than it is in a normally formed tooth.
This can make the tooth more sensitive to:
However, sensitivity is not present in every Turner’s Tooth.
A dentist should assess persistent sensitivity to determine whether it is caused by the enamel defect or another dental problem.
It can.
Healthy enamel provides a strong protective surface around the tooth.
When enamel is thin, pitted, rough, or missing in areas, plaque can accumulate more easily. Some defects may therefore make maintaining the tooth more difficult.
This does not mean that every Turner’s Tooth will develop cavities.
Regular brushing with fluoride toothpaste, cleaning between teeth, dietary care, and professional dental examinations remain important.
Diagnosis usually involves combining the appearance of the tooth with the child’s dental history.
The dentist may ask:
The dentist will then examine the enamel, tooth shape, surrounding tissues, and bite.
Dental X-rays may be used when the dentist needs additional information about the tooth and surrounding structures.
These terms are related but should not always be used interchangeably.
Enamel hypoplasia broadly describes a quantitative defect in enamel development, meaning less enamel may have formed than expected.
Turner’s Tooth refers to a developmental defect affecting a permanent tooth that is associated with a disturbance involving its primary predecessor.
Therefore, Turner’s Tooth can be understood as a specific clinical pattern rather than a term for every type of enamel hypoplasia.
Yes.
Treatment depends on how severely the tooth has been affected.
A small discoloration may require little or no treatment, while a tooth with significant enamel loss may require restorative care.
The dentist considers:
If the defect is mild and the tooth is healthy, the dentist may recommend observation.
Regular examinations allow the dentist to monitor:
Not every Turner’s Tooth requires immediate restorative treatment.
When enamel is weakened or vulnerable, preventive dental care becomes especially important.
A dentist may recommend fluoride toothpaste and, depending on the child’s individual needs and caries risk, professional fluoride treatment.
The objective is to support the health of the remaining enamel and reduce the risk of decay.
If the tooth has grooves or pits that are difficult to clean, a sealant may sometimes be considered.
Sealants can help protect suitable pits and fissures from plaque accumulation.
Whether a sealant is appropriate depends on the specific shape and condition of the tooth.
Composite resin can sometimes be used to repair small enamel defects or improve the appearance of a discolored or irregular tooth.
The dentist can add tooth-colored material to areas where enamel is missing or reshape an affected portion of the crown.
This can provide both cosmetic and protective benefits in selected cases.
For older teenagers or adults with suitable teeth, a veneer may sometimes be considered when the primary concern is a visible enamel defect.
Veneers cover the front surface of the tooth and can improve its color and shape.
The dentist must first assess the amount and quality of remaining tooth structure.
If a permanent tooth has extensive structural damage or significant enamel loss, a crown may be considered.
A crown covers the tooth and can provide additional protection when a simple filling or bonding procedure is insufficient.
However, a crown is not automatically required simply because a tooth has Turner’s Tooth.
If a Turner’s Tooth develops a cavity, the decay needs to be treated separately.
Depending on its depth and extent, treatment may include a filling or more extensive restorative care.
If decay reaches the dental pulp, additional treatment may be necessary.
It depends on the nature of the discoloration.
The color change associated with Turner’s Tooth may be related to changes in enamel development rather than ordinary surface staining.
For this reason, routine whitening may not produce the desired result.
If the discoloration is localized, options such as composite restoration or other cosmetic treatments may provide a more predictable improvement.
A dentist should determine the cause of discoloration before any whitening procedure is considered.
Not every case can be prevented because the developmental disturbance may occur before the permanent tooth erupts.
However, protecting primary teeth is important.
Parents can help reduce the risk of problems affecting baby teeth by:
A baby tooth may eventually fall out, but that does not mean infection or trauma involving it can safely be ignored.
A dental injury involving a primary tooth should be evaluated, particularly when the tooth has been significantly displaced, fractured, or damaged.
The developing permanent tooth is located beneath or near the primary tooth, depending on the stage of development.
A dentist can assess the injury and determine whether monitoring is necessary.
Parents should also watch for later changes when the permanent tooth eventually erupts.
Arrange a dental examination if your child’s permanent tooth:
A developmental enamel defect is easier to manage when the tooth is assessed before significant decay or structural damage develops.
Turner’s Tooth is a developmental enamel defect that can affect a permanent tooth when its development is disturbed by problems involving the primary tooth that came before it.
The affected tooth may appear discolored, pitted, grooved, irregular, or have areas of thin or missing enamel. Although the appearance can be concerning, Turner’s Tooth does not automatically mean the tooth is unhealthy or needs extensive treatment.
The important step is identifying the cause of the unusual appearance. A dentist can distinguish Turner’s Tooth from cavities, staining, fluorosis, and other enamel abnormalities and determine whether the tooth needs monitoring, preventive care, or restoration.
Protecting baby teeth is also important because primary teeth play a role in the healthy development of the permanent teeth beneath them.
If a permanent tooth erupts with unusual discoloration, pits, or weak-looking enamel, having it examined early can help protect the tooth and guide appropriate treatment.
Visit us at-
Dr gowds dental hospital Nanakramguda
Dr gowds dental hospital Gachibowli
Dr gowds dental hospital madhapur
Turner’s Tooth is a developmental defect affecting a permanent tooth, usually associated with a disturbance involving the primary tooth that preceded it. The permanent tooth may develop discolored, pitted, grooved, or deficient enamel.
Turner’s Tooth can develop when a disturbance affecting a primary tooth interferes with the development of the permanent tooth underneath. Severe infection and trauma to a baby tooth are important associated factors.
No. Turner’s Tooth is a developmental enamel defect and is different from tooth decay. However, defective enamel may sometimes make the tooth more susceptible to plaque accumulation and cavities.
Treatment depends on the severity of the enamel defect. Mild cases may only require monitoring and preventive care, while more noticeable or structurally affected teeth may be treated with composite bonding, veneers, crowns, or other restorative approaches.
Yes. If the enamel is thin, rough, or missing in areas, the tooth may become more sensitive to cold, heat, sweets, brushing, or touch.
A severe infection involving a primary tooth can disturb the developing permanent successor and may result in an enamel defect consistent with Turner’s Tooth.
Yes. Trauma to a primary tooth can sometimes affect the developing permanent tooth underneath it. The effect depends partly on the child’s age and the stage of development of the permanent tooth.
Traditional whitening may not correct the underlying developmental defect because the discoloration can result from abnormal enamel formation. Depending on the tooth, restorative or cosmetic treatment may provide a more appropriate solution.
The developmental enamel defect itself does not naturally disappear because it formed as the permanent tooth developed. However, the appearance and function of the tooth can often be managed with appropriate dental care.
Not every case can be prevented, but protecting primary teeth from decay and injury is important. Good oral hygiene, appropriate fluoride use, regular dental checkups, and prompt treatment of primary tooth infections can help protect developing permanent teeth.


 Gachibowli Branch
